Carpal Tunnel Syndrome and Surgery (Hand Numbness)
Carpal tunnel syndrome is compression of the median nerve within a narrow wrist tunnel. Its most typical symptom is hand numbness that wakes you at night; early disease is treated with splinting and adjustments, and advanced disease with a small operation.
Also known as: Carpal tunnel syndrome (CTS), Median nerve compression, Nerve compression at the wrist

Your Treatment Pathway
Examination
Symptom distribution, sensation, thumb muscle strength and wrist tests are assessed.
EMG and Imaging If Required
The degree of compression is measured; conditions causing similar symptoms are distinguished.
Non-Surgical Plan
Night splinting, modifying hand use, injection when needed and control of associated conditions.
Release Surgery If Required
The ligament over the tunnel is divided to relieve nerve pressure; discharge is usually the same day.
Movement and Follow-up
Early finger movement, wound care and monitoring of sensory recovery at follow-up visits.
What Is Carpal Tunnel Syndrome?
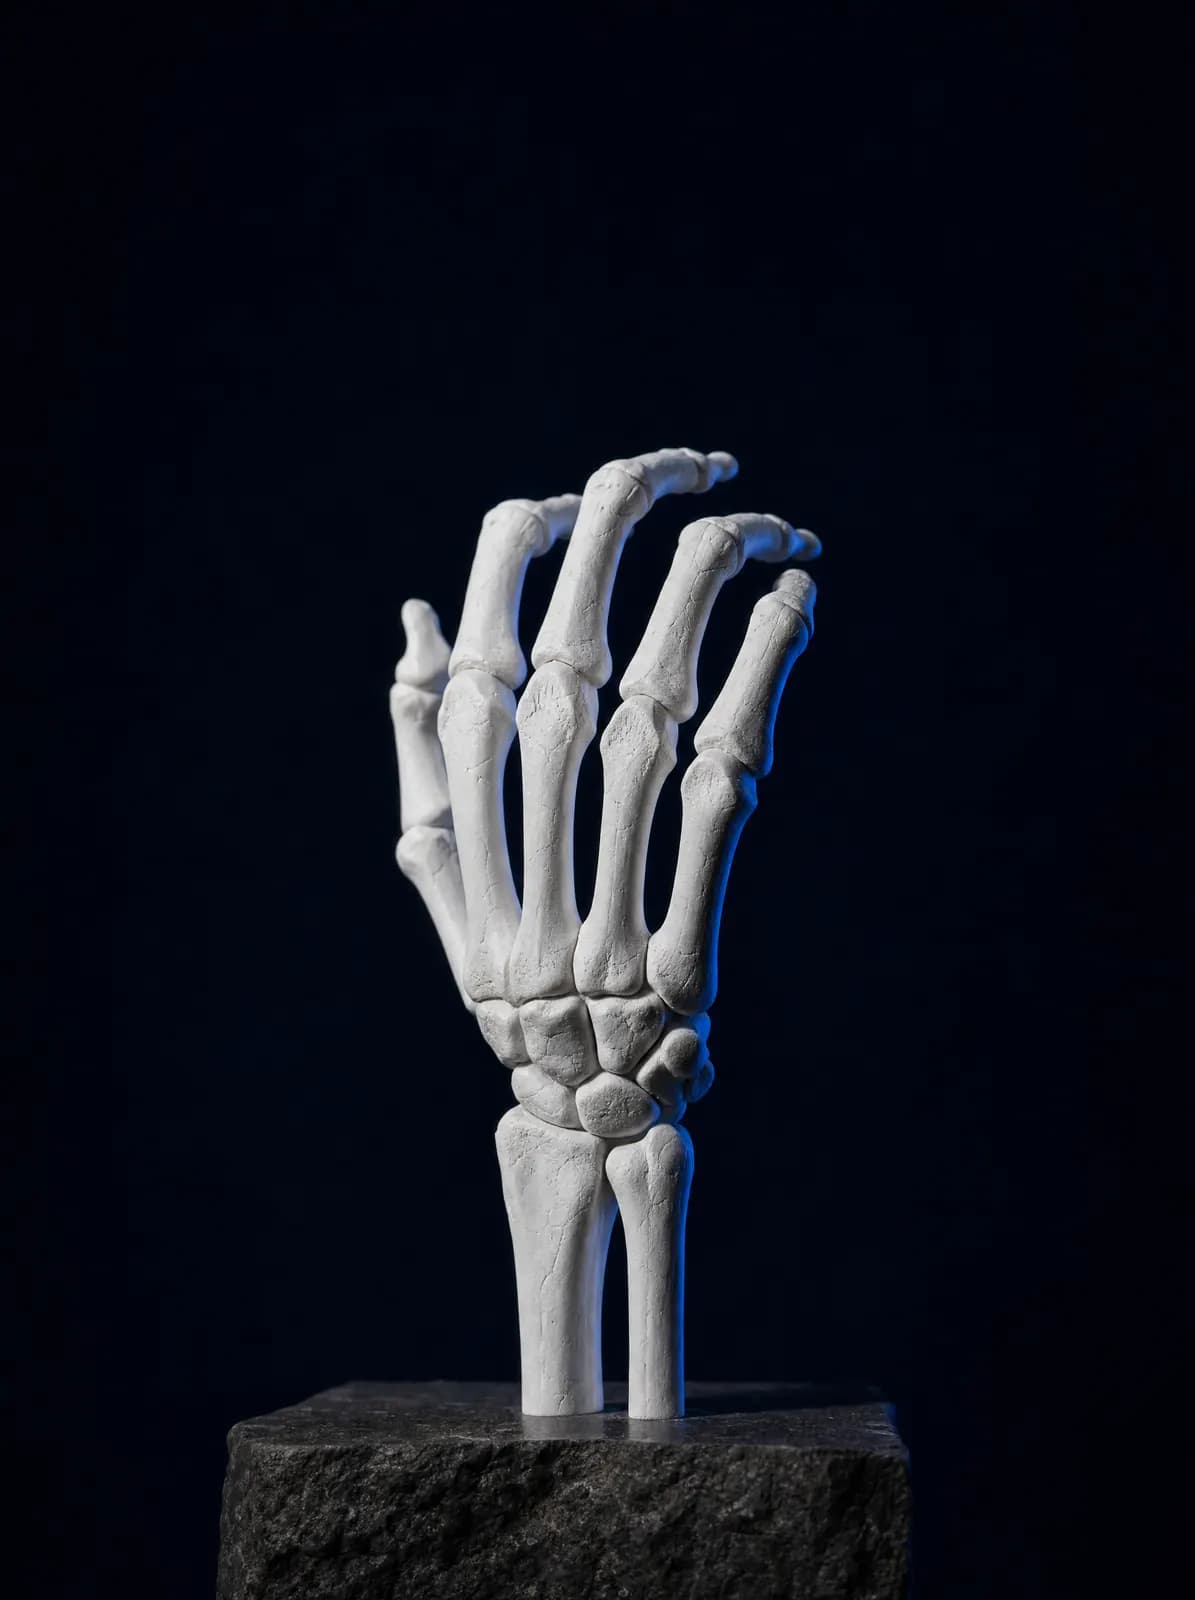
On the palm side of the wrist is a narrow passage formed by wrist bones and a firm covering ligament, the transverse carpal ligament. This is the carpal tunnel. Nine finger-flexor tendons and the median nerve, supplying the thumb, index and middle fingers and half the ring finger, pass through it.
When pressure inside the tunnel increases, the nerve is affected most because tendons tolerate compression better. Pressure first slows conduction, then may affect the nerve's outer sheath and eventually its fibres. This is carpal tunnel syndrome, the most common nerve compression in the hand.
Symptoms usually begin gradually and increase over months. Early symptoms come and go, and even simple adjustments may provide relief at this stage. In longstanding neglected cases, muscle wasting at the base of the thumb and permanent sensory loss can develop, so persistent numbness is a warning that should not be ignored.
What Are the Symptoms?
Most patients describe 'my hand goes numb at night and improves when I shake it'. Common symptoms include:
- Hand and finger numbness, tingling or burning that wakes you at night
- Marked numbness in the thumb, index and middle fingers, usually sparing the little finger
- Temporary relief of symptoms when shaking the hand
- Hand numbness while driving, using a phone or holding a newspaper or book
- Dropping glasses, keys or bags; difficulty fastening buttons and opening jars
- In advanced stages, thinning of the thumb-base muscle bulk and reduced grip strength
What Causes It, and Who Is More Commonly Affected?
Most patients have no single cause; a naturally narrow tunnel and repetitive hand use act together. Known risks include work involving repeated wrist bending and straightening, vibrating tools, agricultural and industrial tasks requiring prolonged gripping, deformity after a wrist fracture, and cysts or lumps occupying space around the wrist.
Systemic causes are also common: diabetes, an underactive thyroid, rheumatic disease, gout, kidney failure and excess weight can raise pressure in the tunnel. Assessment therefore covers associated conditions as well as the hand; treating the underlying disease can sometimes substantially reduce symptoms.
Hand Numbness During Pregnancy
Fluid retention during pregnancy, particularly in the last three months, may increase pressure within the tunnel and cause carpal tunnel symptoms. In most women, this settles spontaneously within weeks after delivery; treatment is generally limited to a night splint and modifying hand use. Persistent symptoms after delivery require reassessment.
How Is It Diagnosed?
Diagnosis starts with history and examination. Finger sensation, thumb muscle strength and bulk, and simple wrist provocation tests are assessed. The description of symptoms, such as night waking and shaking the hand, provides valuable clues.
EMG (electromyography), or nerve conduction testing, objectively demonstrates the presence and severity of compression; it also helps distinguish conditions with similar symptoms, such as a cervical disc herniation, nerve compression at the elbow (cubital tunnel syndrome) or generalised nerve disorders. Ultrasound may be requested if a wrist cyst, mass or thickened tendon sheath is suspected. X-rays are obtained if post-fracture deformity or osteoarthritis of the wrist itself is suspected.
Marked little-finger numbness suggests compression may be at the elbow rather than the wrist. This is specifically assessed because it directly changes treatment planning.
Non-surgical Treatment Options
Mild to moderate symptoms, particularly those worse at night, are initially treated without surgery. A night wrist splint in a neutral position prevents bending during sleep, reduces tunnel pressure and substantially decreases night waking in many patients. It is used particularly at night rather than during the day.
Treatment also includes modifying hand use (avoiding prolonged gripping in one position, taking breaks and limiting time with vibrating tools), short-term anti-inflammatory medication on medical advice, and managing underlying conditions such as diabetes or thyroid disease. Nerve-gliding exercises provide relief for some patients.
If symptoms persist, a corticosteroid injection may be given into the tunnel. It offers temporary relief for many patients and can support the diagnosis, but its effect is time-limited and repetition is restricted. Persistent sensory loss, muscle wasting or severe compression on EMG means that waiting with non-surgical treatment may cause nerve damage that is difficult to reverse.
When Is Surgery Needed?
Surgery becomes more likely when symptoms persist despite non-surgical treatment, numbness becomes constant day and night, or examination and EMG show progressive nerve damage. Once thumb-base muscle wasting begins, treatment is not delayed.
The operation is called carpal tunnel release. The ligament covering the tunnel is divided to relieve pressure on the nerve; the nerve itself is not cut, and the divided ligament heals in a more spacious position. The procedure usually uses a small incision in the palm (open surgery) or an endoscopic technique in suitable cases. Regional anaesthesia numbing only the hand and wrist is often sufficient, and the patient goes home the same day.
The appropriate technique depends on wrist anatomy, previous surgery and accompanying problems. If trigger finger or a ganglion cyst is also present, treating it in the same session is discussed at consultation.
What Is Recovery Like After Surgery?
Night waking improves within the first days in many patients and is usually the earliest symptom to settle after surgery. Fingertip sensation improves over weeks or, in longstanding cases, months, depending on nerve recovery. Limited recovery is discussed beforehand in neglected cases with muscle wasting.
Fingers are moved from the first day after surgery because keeping them still causes stiffness. Keep the hand dry until the wound heals and postpone heavy lifting and forceful gripping for several weeks. Pressure tenderness in the palm ("pillar pain") may last a few months and gradually improves.
Desk work is usually resumed within a few days to two weeks; forceful manual or machine work takes longer. Timing is determined at follow-up according to the person and workload.
What Should You Consider in Daily Life?
Avoid positions that keep the wrist bent for a long time, such as prolonged phone holding, sleeping with a hand under the pillow or typing with a flexed wrist. Short breaks during repetitive gripping, dividing time spent using vibrating tools and wearing gloves reduce load.
Symptoms may become more noticeable during hazelnut harvesting and threshing in Ordu, when prolonged gripping and vibrating-tool use increase. If numbness persists throughout the season and disrupts sleep, assessment at AC CLINIC is recommended without waiting for the season to end.
Frequently Asked Questions
Mild, recent symptoms may improve substantially with a night splint, modified hand use and treatment of underlying conditions. Non-surgical measures have limited effect once numbness is constant or sensory loss or muscle wasting has begun.
The procedure is generally brief and usually performed under regional anaesthesia. Most patients go home the same day; admission depends on coexisting conditions and additional procedures.
Night-time waking often decreases in the first days. Fingertip sensation improves over weeks or months as the nerve recovers. Improvement may remain partial in longstanding neglected cases.
Because operating on both hands together can make daily tasks difficult, the more symptomatic hand is usually treated first. Work, help at home and symptom severity inform the shared decision.
Yes. Cervical disc herniation, nerve compression at the elbow and generalised nerve disorders can cause similar symptoms. The affected fingers, examination and EMG help distinguish them.
You can book an examination by telephone or WhatsApp at AC CLINIC in Altınordu, Ordu. Bring any previous EMG report to help assessment.
References


Appointments and Contact
Call or contact us on WhatsApp to arrange an appointment. Briefly describe your symptoms; we try to schedule your examination and any necessary imaging on the same day.
- Opening hours
- 08:30–18:00Monday – Saturday
The clinic is not a 24/7 emergency department. For a fracture, dislocation, open wound, or inability to bear weight with fever, call 112 or attend the nearest hospital emergency department.